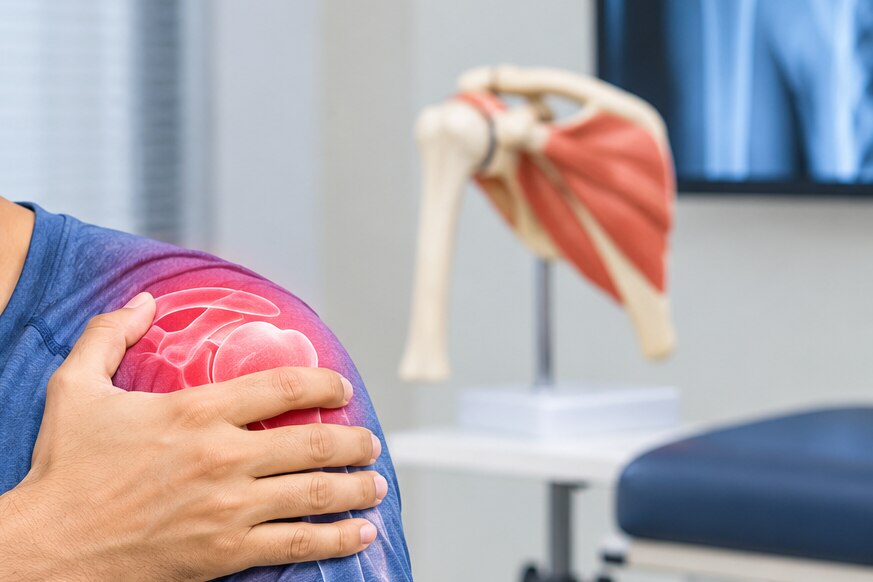
Shoulder pain becomes easier to address when you can describe its pattern, recognise warning signs, and understand what an orthopaedic examination is designed to find. By the end, you will know when home care is reasonable, when to seek prompt review, and why an X-ray, ultrasound, or MRI might be recommended.
Key takeaways
- Track pain location, travel, and triggering movements for three to seven days.
- A neck examination helps identify pain referred to the shoulder.
- Frozen shoulder limits both active and passive movement.
- Discuss treatment when pain persists, worsens, or restricts sleep and daily tasks.
Describe Your Shoulder Pain So the Examination Can Find Its Cause
Record the pattern of your pain for three to seven days before seeking shoulder pain relief. Note where it starts, whether it travels, and which movement changes it; these details help separate a shoulder problem from pain referred by the neck.
- Write down when the pain began and what happened beforehand, including a fall, lifting effort, sports activity, injection, or illness.
- Mark the exact location: top of the shoulder, outer upper arm, front, back, or area near the shoulder blade. Record whether it spreads below the elbow.
- Rate the pain from 0 to 10 at rest, during movement, and at night. Note whether it wakes you or makes lying on one side impossible.
- List movements that trigger it, such as reaching overhead, putting on a shirt, fastening clothing behind your back, lifting, or reaching across your body.
- Record weakness, stiffness, clicking, catching, instability, numbness, or tingling. State whether you can still raise the arm, carry objects, and work normally.
Pain below the elbow, pins and needles, numbness, weakness in one part of the arm, or symptoms changed by turning or bending your neck need a neck and nerve examination as well as a shoulder examination.
Seek orthopaedic review when pain is worsening, movement is becoming harder, or two weeks of sensible self-care has not helped. Bring your notes and a list of medicines, injections, and previous injuries.
What a Bone Specialist Checks During a Gultekdi Consultation
An orthopedic consultation checks more than the painful spot: it tests whether the problem comes from the shoulder joint, tendons, muscles, or neck. A search for “bone specialist Gultekdi” is really a search for this focused assessment, especially when pain worsens, movement becomes difficult, or two weeks of self-care has not helped.
Expect the examination to cover:
- Your pain history: exact location, onset, injury, night pain, clicking, stiffness, weakness, and movements that trigger symptoms.
- Active and passive range of motion: you move the arm, then the examiner moves it, including overhead, behind your back, and across your body.
- Strength and tendon tests: resisted lifting and rotation can expose rotator-cuff irritation or a tear even when an X-ray looks normal.
- Neck, nerve, and joint checks: neck movement, sensation, reflexes, instability, tenderness, and swelling help separate cervical pain, nerve symptoms, arthritis, bursitis, and shoulder disorders.
Marked loss of both active and passive movement points toward frozen shoulder, especially when stiffness progresses. Tell the clinician if you have diabetes: AAOS estimates frozen shoulder affects 10–20% of people with diabetes, compared with about 2–5% of the general population.
Pain below the elbow, tingling, numbness, weakness in a nerve pattern, or pain altered by neck movement shifts attention to the cervical spine.
At Chordiya Clinic, take previous reports and name the movement you cannot perform; that gives the orthopedic assessment something testable. Plain shoulder radiographs are usually the initial study for chronic pain; ultrasound or MRI follows when tendon or other soft-tissue disease remains suspected.
Related service
Consultation Consultation we shall be addressing to your chief complaints and associated health related queries. |
How Frozen Shoulder Differs from Tendon, Joint, and Neck Problems
The key distinction is whether the shoulder remains stiff when someone else moves it. In frozen shoulder, active and passive movement are both restricted, with external rotation usually lost first and most severely.
| Cause | Pattern that points to it | Movement or symptom clue |
|---|---|---|
| Frozen shoulder | Progressive stiffness through painful, freezing, frozen and thawing phases | Difficulty reaching overhead, behind your back or across your body; passive movement is also limited |
| Tendon or bursa problem | Pain outweighs stiffness; passive movement is often near-normal | Pain with lifting or resisted movement, night pain, or weakness suggests rotator-cuff irritation or a tear |
| Joint arthritis | Deep pain with stiffness in both active and passive movement | Grinding, reduced rotation and pain that worsens with use point towards joint wear rather than an isolated tendon problem |
| Neck or nerve problem | Pain originates in the neck or travels away from the shoulder | Pain below the elbow, tingling, numbness, nerve-pattern weakness, or symptoms changed by neck movement requires a cervical-spine examination |
Frozen shoulder differs from arthritis because its stiffness often advances steadily, while arthritis more often produces grinding and joint-line pain. Its recovery can take one to three years, so waiting for spontaneous improvement is not the same as obtaining timely shoulder pain relief.
A corticosteroid injection can reduce pain and improve movement in the short term, particularly when it helps you stretch or participate in physiotherapy. It does not release the contracted capsule or guarantee permanent relief.
If the diagnosis remains uncertain, shoulder radiographs are usually the initial imaging; ultrasound or MRI can assess tendons and other soft tissues when an X-ray does not explain the symptoms.
Which Shoulder Tests Explain Pain That an X-ray Cannot Show
A normal X-ray does not rule out a tendon, bursa, labrum, or joint-capsule problem. It shows bones clearly, so it helps identify arthritis, a fracture, dislocation, bone spurs, or narrowing around the shoulder. It cannot show most soft-tissue causes of pain.
| Test | What it shows best | When it is useful |
|---|---|---|
| X-ray | Bone alignment, arthritis, fracture, dislocation, bone spurs | Usually the first imaging test for persistent shoulder pain |
| Ultrasound | Rotator-cuff tendons, bursa, biceps tendon, fluid, movement during testing | When examination suggests a tendon or bursal problem and the X-ray is unrevealing |
| MRI | Rotator-cuff tears, labrum, cartilage, joint capsule, marrow, and deeper soft tissue | When symptoms persist, weakness is substantial, or ultrasound cannot answer the clinical question |
An ultrasound or MRI finding is not automatically the source of your pain. Rotator-cuff tears can exist without symptoms, so a specialist must match the scan with your weakness, movement limits, injury history, and examination findings.
Start with an orthopedic consultation when pain is worsening, shoulder movement is becoming difficult, or two weeks of self-care has not helped. The examination determines whether imaging is needed and which test can guide shoulder pain relief, rather than ordering every scan at once.
MRI is not automatically better than ultrasound; the right choice depends on the suspected structure and the decision treatment must support.
When to Stop Waiting and Discuss Treatment Options
Arrange an orthopedic consultation when shoulder pain is worsening, movement is becoming difficult, or two weeks of sensible self-care has not helped. The search phrase shoulder pain relief bone specialist gultekdi should not distract you from the real triggers: persistence, loss of function, and increasing night pain.
Frozen shoulder can progress through painful, freezing, frozen and thawing phases, with recovery taking one to three years. Waiting for it to resolve is not the same as obtaining timely shoulder pain relief.
Seek prompt assessment if you have:
- Major trauma followed by deformity, sudden inability to use the arm, or severe swelling
- Numbness, tingling, or weakness extending below the elbow, especially when neck movement changes the pain
- Marked stiffness, particularly if you have diabetes; 10–20% of people with diabetes develop frozen shoulder, compared with about 2–5% of the general population
- Shoulder pain with chest discomfort, breathlessness, sweating, or nausea; call emergency services because this pattern can signal a heart problem
Treatment follows the cause and examination findings. Options include activity changes, pain medicine, supervised physiotherapy, and stretching. A corticosteroid injection can reduce frozen-shoulder pain and improve movement short term, helping you participate in physiotherapy, but it does not remove the contracted capsule or guarantee lasting relief.
A significant tendon tear, instability, or advanced arthritis may require surgical discussion after the orthopedic consultation.
Frequently asked questions
How should I describe shoulder pain before a consultation?
Record the pain’s location, whether it travels, which movements trigger it, and how it affects sleep or daily activities for three to seven days.
What does a bone specialist check during a shoulder consultation?
The examination can include shoulder range of motion, strength, tenderness, joint stability, posture, and neck movements to identify referred pain.
How is frozen shoulder different from tendon, joint, and neck problems?
Frozen shoulder restricts both active and passive movement, while tendon problems often weaken specific movements, joint problems cause local pain or stiffness, and neck problems can send pain into the shoulder or arm.
Which shoulder tests can show problems an X-ray cannot?
Ultrasound can assess tendons and bursae, while MRI can show rotator-cuff tears, labral injuries, cartilage damage, and other soft-tissue problems.
When should I discuss treatment for shoulder pain?
Arrange an orthopedic consultation when pain persists, worsens, disrupts sleep, limits daily activities, follows an injury, or comes with weakness, numbness, fever, or visible deformity.
Keywords